
Prostate Cancer: From PSA to MRI, Understanding the Diagnostic Pathway Before Discussing Surgery
An elevated PSA does not automatically mean cancer. Learn how PSA, clinical exam, multiparametric MRI, and targeted biopsy fit together.

Dr Najib Abakka
Urological Surgeon in Rabat

Intégration du dosage du PSA, de l'IRM multiparamétrique et de la biopsie ciblée
PSA: Clinically useful, but not self-sufficient
Prostate-Specific Antigen (PSA) is produced by normal and abnormal prostatic tissue. An elevated level must be interpreted with context: age, prostate volume, family history, symptoms, medications, recent infections, and PSA velocity over time. European Association of Urology (EAU) guidelines stress that no single absolute threshold confirms cancer on its own.
In asymptomatic men with moderately elevated readings, a repeat confirmatory test is often advised before initiating further invasive steps. Medical decisions should never rely on an isolated number.
How multiparametric MRI transformed prostate diagnosis
When significant disease is suspected, multiparametric MRI (mpMRI) identifies abnormal lesions and rates their suspicion using the PI-RADS classification. Guidelines recommend mpMRI prior to biopsy in suspected localized disease.
However, PI-RADS scoring does not replace clinical judgment. High PI-RADS increases suspicion, but a non-suspicious MRI does not reduce risk to absolute zero. PSA density, digital rectal examination, family history, and MRI findings must be interpreted collectively.
The conclusive role of targeted biopsy
Prostate biopsy remains the definitive procedure confirming tissue histology and tumor grade (ISUP Gleason grade). When MRI identifies a discrete target, targeted cognitive or fusion biopsies provide superior diagnostic accuracy.
Only following histological confirmation—and staging imaging when indicated—can therapeutic choices (active surveillance, surgery, radiation) be meaningfully discussed.
Importance for men of African descent
European guidelines recommend initiating informed screening discussions earlier (from age 45) for higher-risk groups, notably men of African ancestry or those with a positive family history. This does not mean everyone requires biopsy, but that risk discussions should begin sooner.
For international patients traveling from West or Central Africa to Rabat, providing historical PSA records alongside MRI and biopsy pathology reports is immensely valuable.
Frequently asked questions
Does an elevated PSA always mean cancer?
No. Benign enlargement, prostatitis, or recent urinary catheterization can elevate PSA. Interpretation must always account for total clinical context.
Does MRI replace the need for biopsy?
No. MRI guides and targets biopsies, but tissue analysis remains essential to confirm tumor presence and aggressiveness.
At what age should men discuss PSA screening?
This depends on personal risk profile. EAU guidelines suggest an informed dialogue starting at age 45 for men of African descent or with familial history, and 50 for average-risk men.
Related guides & articles
Browse all articles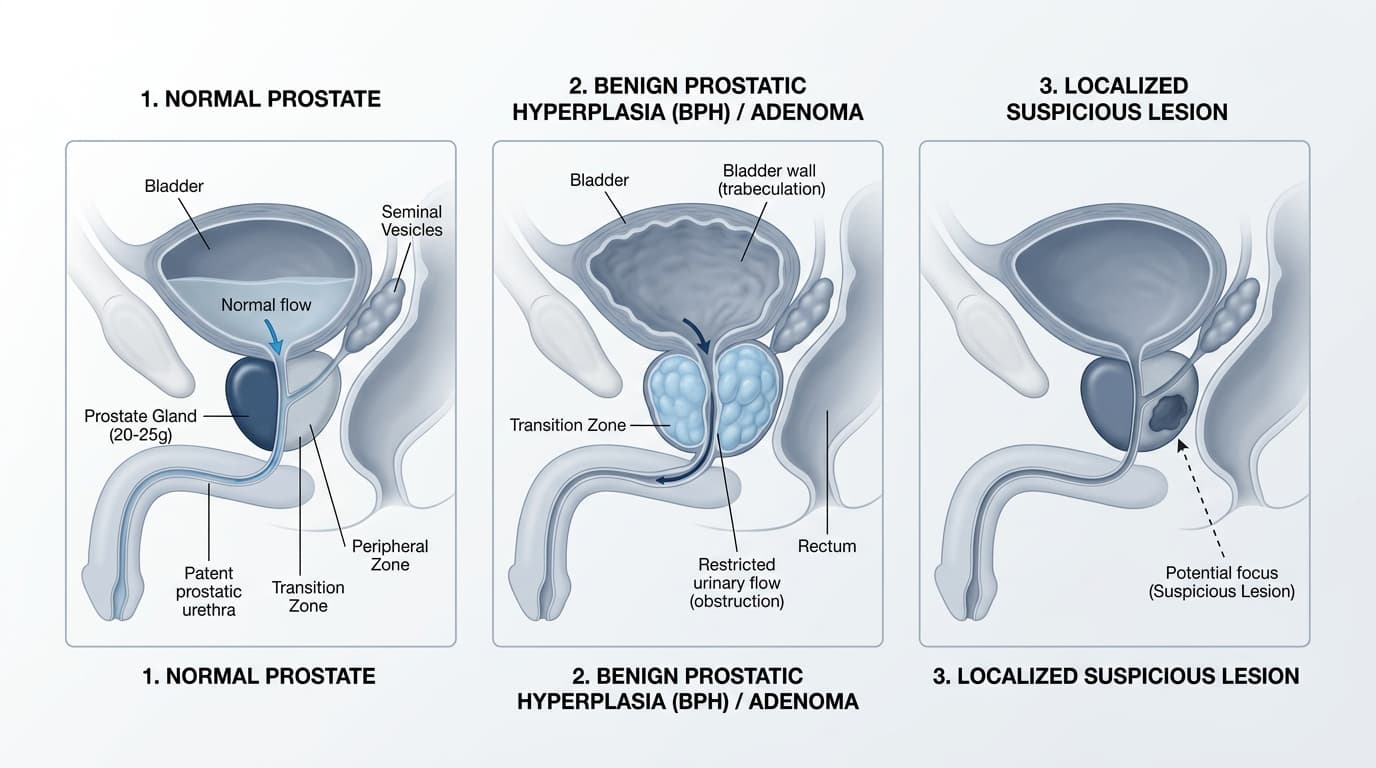
Prostate Adenoma (BPH) or Cancer? Overlapping Symptoms and Distinguishing Tests
Weak stream, nocturnal urination, PSA: benign prostatic hyperplasia and prostate cancer cannot be diagnosed on symptoms alone.

Life After Prostate Surgery: Continence, Sexual Health, PSA, and Follow-Up
What to expect after radical prostatectomy? Catheter care, urinary continence, erectile recovery, pathology results, and PSA monitoring.
Robotic Surgery in Urology in Rabat: What Patients Should Know Before Deciding
Understand robot-assisted urological surgery, its clinical indications, limits, and essential questions to ask before deciding.